Top challenges in administering NIV today – and 5 ways to overcome them
—By Winnie Sywulak, BS, RRT-NPS, Senior Marketing Manager, Respiratory Care Solutions, Draeger, Inc.
Non-invasive ventilation (NIV) has been shown to be effective in avoiding intubation and improving survival in patients with acute hypoxemic respiratory failure compared to conventional oxygen therapy. However, NIV is associated with high failure rates due, in most cases, to patient discomfort.i
So why does NIV fail for some patients? One of the primary reasons is mask intolerance.ii
Researchers have found “the higher the patient’s perceived comfort, the higher the likelihood of compliance with treatment;” therefore, “ensuring patient comfort is an important objective during NIV therapy.”iii
Here are five ways to improve mask comfort and fit for effective NIV administration, greater patient satisfaction and enhanced outcomes.
1. Properly fit the mask
A properly fitted NIV mask will help facilitate effective oxygen delivery and may contribute to improved patient comfort and satisfaction. But there is no one size fits all approach because patient anatomy can vary greatly.
Be sure to select the right mask size by using sizing gauges supplied by the mask manufacturer. Select a mask featuring an individually adjustable cushion, which allows the clinician to achieve an anatomical fit and effective seal. Selecting the correct type of interface greatly reduces painful skin breakdown and ulcerations.
2. Manage mask air leaks
Mask leaks are an inherent part of delivering NIV to patients. While intentional air leaks are incorporated in mask design and NIV circuits to permit CO2 removal,iv unintentional air leaks around the edge of the mask may result in inadequate inspiratory flow demand.
Therefore, managing leaks around the patient interface with a properly sized and fitted patient mask also requires a ventilator that can meet both patient and clinician requirements. The device should be able to meet and exceed the patient’s flow demand all while in the presence of leaks. This combination may help improve patient comfort and ultimately successful NIV.
3. Assess skin integrity
An analysis of medical-device-related pressure ulcers found 70% of the wounds caused by medical devices occurred on the head, face and neck.v Face masks for NIV have been associated with a high percentage of pressure ulcers, for which Medicare denies payment.vi
To prevent pressure ulcers from forming, clinicians should regularly remove the patient’s mask and examine the skin looking for redness, irritation and breaks in the skin.
4. Consider a skin barrier
For patients with skin irritation from the mask and/or for those who are at increased risk for pressure ulcers (e.g., age 60+, type-2 diabetes),vii clinicians should consider the use of hydrocolloid and gel sheets that can be placed between the skin and NIV mask.
Research has shown hydrocolloid dressings placed over the nasal bridge in patients requiring NIV reduced the risk of developing grade 2 pressure ulcers.viii Some masks feature built-in silicone gel technology to help reduce complications, such as pressure points and skin irritation.
5. Alternate mask types
Selecting the correct type of interface greatly reduces painful skin breakdown and ulcerations. For longer NIV therapy, it is recommended to alternate between different mask interfaces to decrease skin breakdown by varying the pressure points on the skin. An alternating interface strategy not only reduces the points of highest pressure, but also improves NIV tolerance and efficacy.ix,x
Conclusion
The proper face mask design and fit can have a significant impact on NIV delivery – but the ventilator is as critically important. You need the right mask paired with the right device to meet your patient demands.
Select a NIV ventilator that is compatible for use with high-quality masks that are available in a wide range of sizes and shapes and can be adjusted to patient anatomy.
A ventilator that supports all modes of invasive and noninvasive ventilation allows a greater degree of treatment options for the patient. It also streamlines clinical workflows, especially for those patients that may need to escalate from NIV to invasive ventilation without delay.xi

Non-Invasive Ventilation Masks
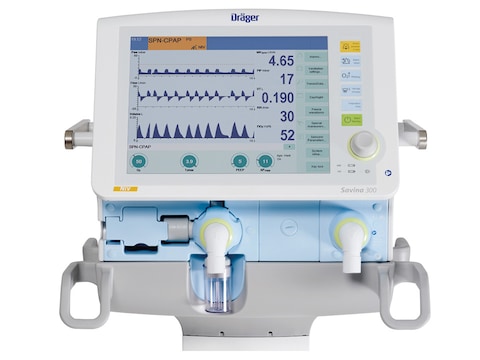
Dräger Savina® 300 NIV (Non-Invasive Ventilation)
As non-invasive as possible, as invasive as necessary. The Savina 300 NIV with automatic leak compensation effectively supports non-invasive ventilation. The built-in-turbine with rapid response time and external battery allows operation independently from the central gas supply.
References
i Cammarota G, Simonte R, De Robertis E. Comfort During Non-invasive Ventilation. Front Med (Lausanne). 2022 Mar 24;9:874250. doi: 10.3389/fmed.2022.874250. PMID: 35402465; PMCID: PMC8988041.
ii Squadrone E, Frigerio P, Fogliati C, et al. Noninvasive vs invasive ventilation in COPD patients with severe acute respiratory failure deemed to require ventilatory assistance. Intensive Care Med. 2004;30(7):1303-1310. doi:10.1007/s00134-004-2320-7
iii Roca O, Masclans JR. Interfaces in non-invasive ventilation: one mask doesn't fit all. Minerva Anestesiol. 2015;81(5):478-479.
iv Roca O, Masclans JR. Interfaces in non-invasive ventilation: one mask doesn't fit all. Minerva Anestesiol. 2015;81(5):478-479.
v Medical Devices’ Role in Causing Pressure Ulcers, ECRI, August 1, 2014, https://www.ecri.org/components/PSOCore/Pages/PSONav0814.aspx?tab=2
vi Visscher MO, White CC, Jones JM, Cahill T, Jones DC, Pan BS. Face Masks for Noninvasive Ventilation: Fit, Excess Skin Hydration, and Pressure Ulcers. Respir Care. 2015;60(11):1536-1547. doi:10.4187/respcare.04036
vii Kaur R, Patel A, Pipkins J, Garcia Y, Elshafei A, Reducing the Incidence of Noninvasive Face Mask-Related Skin Breakdown, Respiratory Care Oct 2021, 66 (Suppl 10) 3602142;
viii Bishopp A, Oakes A, Antoine-Pitterson P, Chakraborty B, Comer D, Mukherjee R. The Preventative Effect of Hydrocolloid Dressings on Nasal Bridge Pressure Ulceration in Acute Non-Invasive Ventilation. Ulster Med J. 2019;88(1):17-20.
ix Hilbert G, Gruson D, Gbikpi-Benissan G, Cardinaud JP. Sequential use of noninvasive pressure support ventilation for acute exacerbations of COPD. Intensive Care Med. 1997;23:955–961.
x Ozyilmaz E et al. Timing of noninvasive ventilation failure: causes, risk factors, and potential remedies. BMC Pulm. Med. 2014; 14:19
xi Rochwerg B, Brochard L, Elliott MW, Hess D, Hill NS, Nava S, Navalesi P Members Of The Steering Committee, Antonelli M, Brozek J, Conti G, Ferrer M, Guntupalli K, Jaber S, Keenan S, Mancebo J, Mehta S, Raoof S Members Of The Task Force. Official ERS/ATS clinical practice guidelines: noninvasive ventilation for acute respiratory failure. Eur Respir J. 2017 Aug 31;50(2):1602426. doi: 10.1183/13993003.02426-2016. PMID: 28860265.